
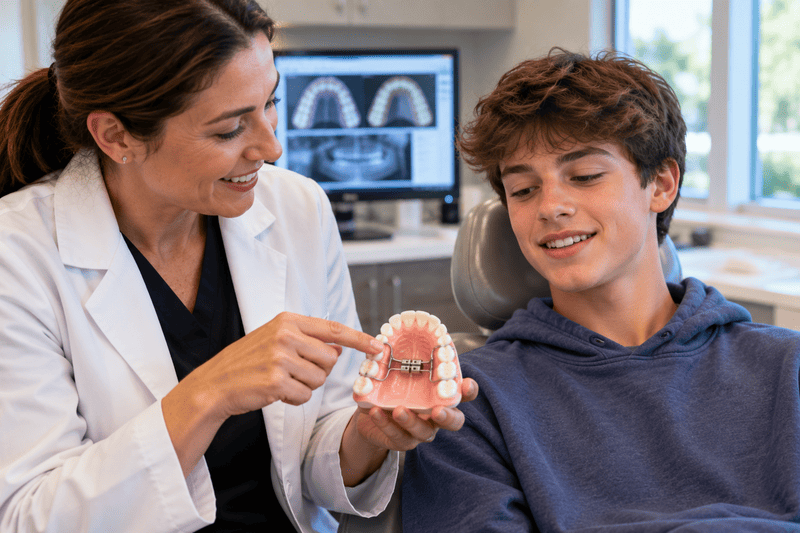
Miniscrew-assisted rapid palatal expansion (MARPE) and conventional rapid palatal expansion (RPE) are orthodontic treatments used to correct a narrow upper jaw, also known as transverse maxillary deficiency. Both appliances are designed to widen the maxilla, but they use different methods to deliver expansion forces. Conventional RPE primarily relies on the teeth for anchorage, while MARPE uses small temporary miniscrews placed in the palate to provide additional skeletal anchorage. For some teenagers, particularly those who are older or further along in skeletal development, MARPE may provide advantages over conventional RPE.
One important advantage of MARPE is its ability to produce more skeletal expansion. Conventional RPE transfers much of its force through the teeth and surrounding dental structures. As teenagers mature, the midpalatal suture and other facial sutures become more resistant to expansion. Research suggests that conventional RPE is most predictable at younger ages, while its effects can become less predictable after puberty. MARPE is designed to direct more of the expansion force toward the maxillary bone, potentially allowing greater skeletal expansion in older adolescents.
Another potential benefit is reduced dental side effects. Because conventional RPE is primarily supported by the teeth, expansion can result in some outward tipping or movement of the teeth. Research comparing MARPE with conventional RPE has found that MARPE generally produces greater skeletal expansion and fewer undesirable dental and periodontal effects, although it can still produce dental and periodontal changes.
MARPE may also be beneficial when the goal is to correct an underlying skeletal deficiency rather than simply moving the teeth outward. By using miniscrews as anchorage, the appliance can apply forces closer to the palate and maxillary bone. This can help create a wider upper jaw and may improve the transverse relationship between the upper and lower jaws. Correcting this deficiency can also help address orthodontic problems such as posterior crossbite and dental crowding.
Another potential consideration is the nasal airway. Since the maxilla forms part of the floor and lateral boundaries of the nasal cavity, skeletal expansion can produce changes in the nasal region. Studies have reported increases in nasal cavity dimensions following MARPE, although the relationship between anatomical changes and actual breathing or sleep-disordered breathing symptoms is variable. Therefore, MARPE should not be considered a guaranteed treatment for airway problems.
However, MARPE is not automatically better for every teenager. Younger adolescents may respond very well to conventional RPE because their midpalatal sutures are less mature. MARPE also requires miniscrew placement, which introduces additional considerations such as hygiene, temporary discomfort, and the possibility of miniscrew-related complications. The quality of evidence regarding MARPE also remains limited in some areas, with researchers noting the need for more high-quality, long-term studies.
In conclusion, MARPE may offer important benefits for selected teenagers, particularly older adolescents with a significant skeletal maxillary deficiency. Its ability to provide skeletal anchorage may allow greater orthopedic expansion while reducing some unwanted dental effects associated with conventional RPE. However, the most appropriate appliance depends on the individual’s skeletal maturity, anatomy, amount of maxillary constriction, and orthodontic goals. A thorough orthodontic evaluation is therefore essential before deciding between MARPE and conventional RPE.